In addition to today’s resource, please review 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines [PubMed Abstract] [Full-Text HTML] [Full-Text PDF]. J Am Coll Cardiol. 2026 May 19;87(19):2624-2757. doi: 10.1016/j.jacc.2025.11.016. Epub 2026 Mar 13.
The above article has been cited by 113 articles in PubMed.
Today, I review, link to, and excerpt from The Curbsiders’ “#541 A Walk Through the 2026 Lipid Management Guidelines.*
*Gorth DJ, Edmundowicz D, Williams PN, Watto MF. “#541 A Walk Through the 2026 Lipid Management Guidelines”. The Curbsiders Internal Medicine Podcast. thecurbsiders.com/category/curbsiders-podcast October 5, 2026.
All that follows is from the above resource.
Transcript available via YouTube
Cardiovascular disease caused by hyperlipidemia is the leading cause of death worldwide, but it doesn’t have to be! We have the tools to treat this widespread problem. Dr. Daniel Edmundowicz (Temple University) takes us through how to keep lipids where they should be, low.
Claim CME for this episode at curbsiders.vcuhealth.org!
Patreon | Episodes | Subscribe | Spotify | YouTube | Newsletter | Contact | Swag! | CME
Show Segments
- Intro
- Case
- Topic
- Rapid fire questions/Picks of the Week
- Outro
Disclosures
Dr. Edmundwicz reports no relevant financial disclosures. The Curbsiders report no relevant financial disclosures.
Lipid Management Pearls
- Managing lipids properly would prevent many deaths from the leading cause of mortality.
- The cornerstone of assessing risk to guide the initiation of lipid lowering therapy is the PREVENT risk algorithm, which predicts the risk for incident cardiovascular disease in adults 30 to 79 years of age.
- There is a clear asymmetric risk when you weigh the substantial harm of a cardiovascular event against the exceedingly minimal risk of starting a statin therapy that you can always stop.
- To accurately assess cardiovascular risk in women, you need to think of the obstetrical history as a cardiovascular history. Preeclampsia, gestational hypertension/diabetes, premature delivery, and premature menopause are all cardiovascular risk enhancers.
- A “normal” lipid panel should not be reassuring; “normal” means that they are average compared to a population that dies overwhelmingly from atherosclerotic vascular disease.
- CAC score ≥ 100, indicating subclinical atherosclerosis, should prompt consideration of treatment with statin therapy.
- In patients unable to reach treatment goals on statin monotherapy, combination therapy that hits a different mechanism of action can have a synergistic effect.
- You should consider testing for familial hypercholesterolemia (FH) if a patient’s LDL-C ≥ 160 mg/dL without an identified secondary cause.
Lipid Management
Why you should care about lipids
Coronary artery disease caused by atherosclerosis is THE leading cause of death worldwide (Global burden of Disease 2023). And, elevated low-density lipoprotein concentration is unequivocally the cause of atherosclerosis (Ference et al 2017). Many premature deaths are likely preventable by lifestyle and medication interventions (INTERHEART study). That means that we have the tools to prevent a substantial portion of the deaths from the leading cause of mortality (McKinley et al 2021). In short, you should care about managing lipids because, to quote Dr. Edmundowicz quoting Willie Sutton, “that’s where the [mortality modifying] money is.”
Stratifying Risk to Guide Treatment
Broadly speaking, risk stratification is done to establish the likelihood of an adverse event to balance that negative outcome against the inherent risk of a preventative intervention. The cornerstone of assessing risk to guide the initiating lipid lowering therapy (LLT) is the PREVENT risk algorithm, which predicts the risk for incident cardiovascular disease in adults 30 to 79 years of age without known ASCVD (Khan et al 2023).
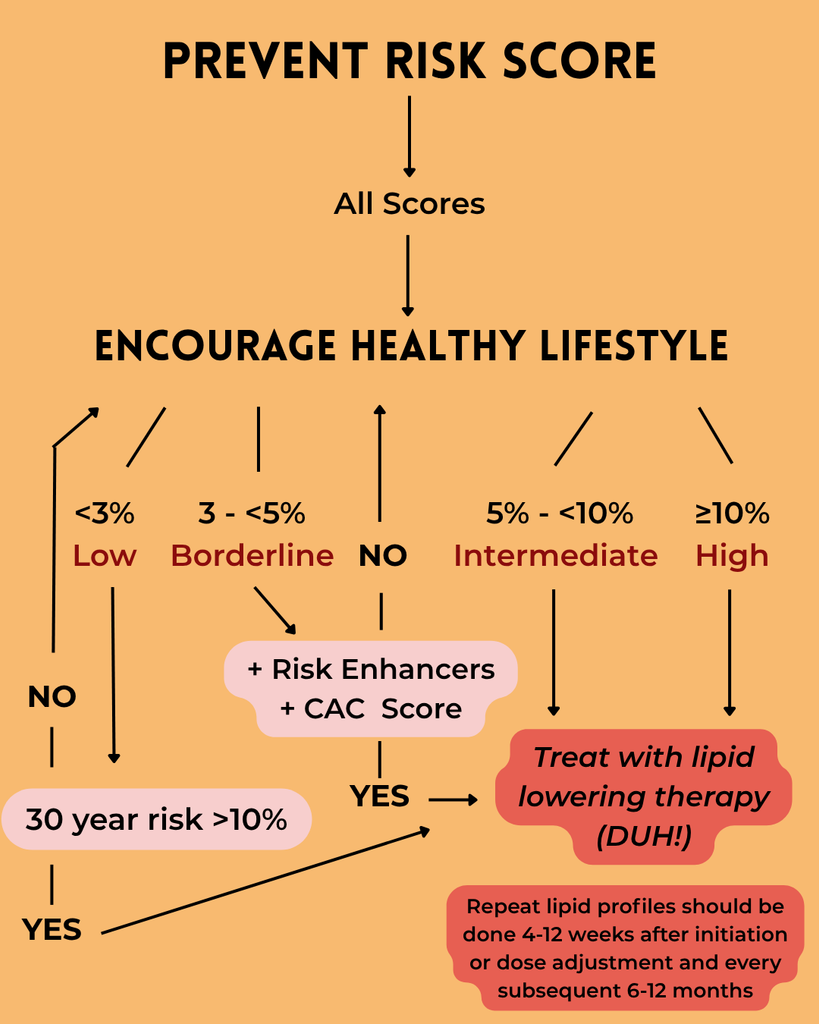
The approach to lipid management is based on the patient’s 10-year risk score broken down as follows: low <3%, borderline (3-<5%), intermediate (5%-<10%), or high risk ≥ 10%. NB: interventions to lower lipids are extremely safe; the risk of exercise is low (please wear a helmet while biking) and statins are one of the safest medications available. The net benefit threshold to start statins is very low (3% risk cut off!) (CTT collaborators 2012). There is a clear asymmetric risk when you weigh the substantial harm of a cardiovascular event against the exceedingly minimal risk of starting a statin therapy that you can always stop. The earlier that you start modifying lipids with statins the more time you have to push back the course of disease.
It is a no-brainer to start a statin for individuals with intermediate and high risk (COR 1) (Blumenthal et al, 2026). But, it is important to think about risk beyond the 10-year risk score. If your patient has a low (<3%) 10-y risk but a high (>10%) 30-y risk, treatment with a moderate intensity statin is reasonable (COR 2a). For patients with borderline risk, the decision to start a statin should be based on risk enhancers like premature ASCVD in a first degree relative (<55yo men or <65yo in women), chronic inflammatory disease, elevated Lp(a) (> 125 nmol/L or > 50 mg/mL), or reproductive risk markers (preeclampsia, gestational diabetes, gestational hypertension, premature delivery, and early menopause). To accurately assess cardiovascular risk in women, you need to think of the obstetrical history as a cardiovascular history. Patients who also carry a diagnosis of HIV, T2DM (≥ 30 yo), or CKD stage 3 or higher should also receive lipid lowering therapy regardless of their PREVENT-ASCVD score (COR 1).
It is hard to convince patients to fix something that they do not perceive as broken. To help frame the cardiovascular disease, Paul Nelson Williams, America’s Primary Care Doctor™, pulls up any non-contrast CT with the heart included to show patients the calcium in their coronaries, providing a visual touch point to understand their risk. It turns out that this technique is supported by research and was shown to increase adherence (Kalia et al 2012). Furthermore, Dr. Edmundowicz reminds us that a “normal” lipid panel should not be reassuring; “normal” means that they are average compared to a population that dies overwhelmingly from atherosclerotic vascular disease.
Lp(a) and ApoB
All adults should get their Lp(a) tested at least once in their lifetime (COR 1), as it can identify those at higher risk of ASCVD and indicate the need for more intensified LDL and risk factor management (Blumenthal et al, 2026). ApoB is a surface protein marking all plaque-causing lipoproteins, and measuring its concentration provides a reliable marker of ASCVD risk (Marston et al 2021). ApoB can predict residual risk in statin treated patients (Johannesen et al 2021), and its concentration should be used in patients with elevated triglycerides already on lipid lowering therapy to guide further intensification once lipid goals are achieved (COR 2a).
Assessment of Subclinical Coronary Atherosclerosis AKA Coronary Artery Calcium Scoring AKA CAC
The coronary artery calcium (CAC) score uses the presence of calcium in the arteries as a surrogate for atherosclerosis, and a non-zero CAC score indicates the presence of atherosclerosis (Greenland and Lloyd-Jones 2021). CAC imaging can be useful in individuals with intermediate risk or select individuals with borderline risk where the decision to initiate therapy is uncertain (COR 1), and is generally used for men ≥ 40 years old or women ≥ 45. For these patients, lipid-lowering treatment is recommended if CAC > 0, and particularly if CAC ≥ 100 AU or ≥75th percentile (COR 1). Additionally, patients with a noncardiac CT with incidental finding of coronary artery calcification should be considered in treatment decisions. There are now clear recommendations for patients (men ≥ 40 or women ≥ 45) with subclinical coronary atherosclerosis identified in imaging: a CAC score ≥ 100 should prompt treatment with statin therapy (COR 1), and any incidental finding of coronary artery calcification on a noncardiac CT can also prompt treatment (COR 2a).
Dr. Edmundowicz reminds us that a CAC = 0 in young individuals is not reassuring, it is expected, but a zero calcium score in an 70yo would make him stop talking about lipids–that is if Dr. E is constitutionally able to stop talking about lipids. CAC score can be repeated in 3-7 y after a zero calcium score (COR 2a). There is no utility in repeating the calcium score once it is positive. In fact, aggressive treatment of lipids actually increases the calcium score because the plaque gets more dense as the cholesterol leaches out (Xian et al 2021).
Interesting aside: The Healthy Women Study, a long longitudinal study of older women, found that postmenopausal elevation of cholesterol had no predictive value on CAC, but premenopausal LDL did (Matthews et al 2007).
Treatment goals
Now that we have established that everyone should be on lipid lowering therapy (LLT)–maybe we should just add them to the water, trace amounts have already been found in Chicago’s water supply–the question shifts to what therapy to prescribe to our patients. Statins are the cornerstone of LLT, and Dr. Edmundowitz likes to begin by reaching for rosuvastatin 5 mg and uptitrate from there due to rosuvastatin’s pharmacokinetic properties (Table 7 of Blumenthal et al, 2026).
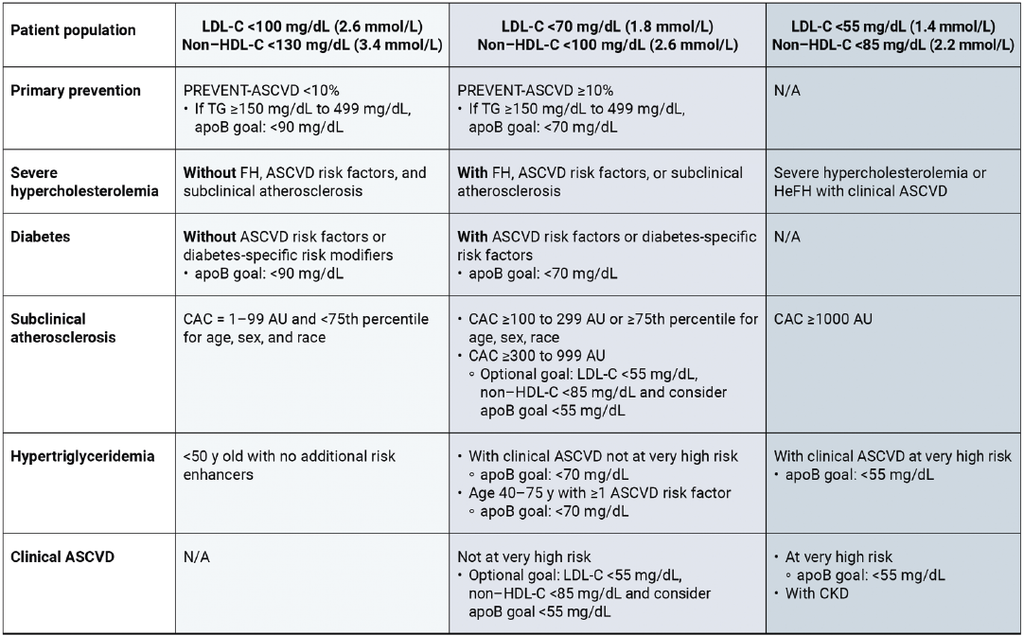
Dr. Edmundowicz tends to be aggressive with his treatment numbers. The guidelines recommend a >50% LDL-C reduction in patients with (higher) intermediate and high risk (COR 1), and refer to upper limit targets in Figure 1 below (Blumenthal et al, 2026). They technically do not recommend number/percentage to keep the LDL-C above. LDL at birth is ~30 mg/dL (Bogsrud et al 2025) indicating that we don’t need a lot in our blood. Interestingly, fibroblasts downregulate LDL receptors when their milieu is around 30 mg/dL of LDL cholesterol (Brown et al 1975). Or per Dr. Edmundowicz’s commentary “Just get everyone’s LDL-C to 30 mg/dL, you’ll be fine” (!! Is he joking? Maybe? Yes? No?) (Karagiannis et al 2026).
Figure 1: Lipoprotein Goals for ASCVD Risk Reduction. Source: 2026 Guideline on the Management of Dyslipidemia (Blumenthal et al, 2026)
In patients with statin intolerance, the guidelines recommend ruling out secondary causes, ensuring that it is not a severe myopathy, and a benefit-risk discussion about continuing statin therapy (COR 1). The way that Dr. Edmundowicz navigates this in practice is to stop the statin for a week while keeping a symptom journal. If the symptoms go away, start the same statin at the same dose. You could also pick a different statin or do alternate day statin therapy–it is even possible to manage some patients on twice weekly statin with daily ezetimibe. Although not in the guidelines, there is data to suggest that co-enzyme Q supplementation (400 mg BID) can be helpful to mitigate myalgia in patients with statin intolerance (Ahmad et al 2024). In patients unable to reach treatment goals, combination therapy that hits a different mechanism of action can have a synergistic effect, ex: ezetimibe 10 mg and rosuvastatin 5 mg. In clinical practice, patients sometimes do not want to take multiple medications, but Dr. E finds that if you explain that you are minimizing side effects and maximizing their benefits patients are more open to the “pill sandwich.”